

Hemoglobin (Hb or Hgb) is an iron-containing protein found in red blood cells, which carries oxygen from the lungs to different tissues of the body. This oxygen is utilised by the cells for energy production. The normal supply of oxygen to the body tissues depends on the oxygen-carrying function of Hb.
The amount of Hb present in a given volume of whole blood is referred to as “hemoglobin concentration”. It is generally expressed in grams per deciliter (g/dL). A blood test measures this concentration rather than the protein as a separate substance.
When the Hb concentration is low, the oxygen-carrying capacity of blood may decrease. High levels may also indicate certain clinical conditions. The measurement of Hb is used to assess blood-related abnormalities, but the interpretation of the result depends on the appropriate reference range, age, sex and clinical condition of the individual. An abnormal Hb value alone cannot identify the underlying disease.
Structure of Hemoglobin
Hemoglobin (Hb) is a globular protein made up of four polypeptide chains, each containing an iron-containing heme group. The molecular structure of Hb consists of the following components:
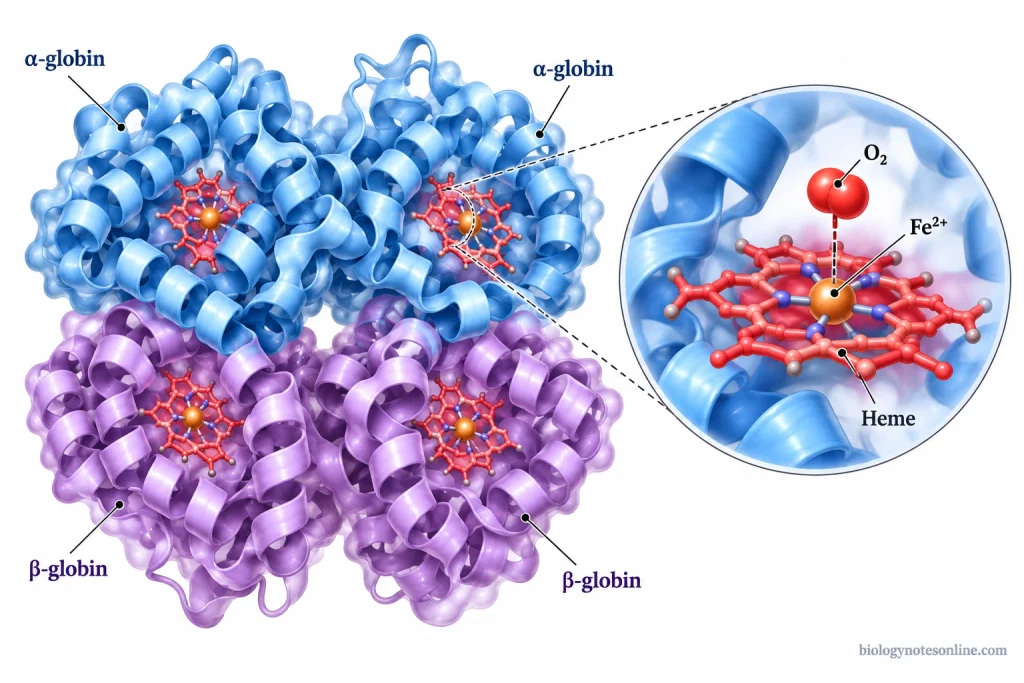
- Globin Chains- A Hb molecule consists of four polypeptide chains, which are arranged in a tetrameric structure. In the major adult form, two alpha (α) and two beta (β) chains are present. Each chain is folded into a compact structure, mainly consisting of alpha-helical regions.
- Arrangement of Globin Chains- One α and one β chain come together to form a pair (dimer). Two such pairs are associated with each other, forming the four-subunit structure of Hb. This arrangement is referred to as the “quaternary structure” of the protein.
- Heme Group- Each globin chain contains a non-protein component called the “heme group”. It is present within a pocket of the folded globin chain. The heme group is made up of a porphyrin ring with a central iron ion in its ferrous state (Fe²⁺). There are four heme groups in a single Hb molecule.
- Oxygen-Binding Sites- The iron atom present in each heme group can reversibly bind one oxygen molecule (O₂). Since four heme groups are present, a single Hb molecule can carry a maximum of four O₂ molecules at a time.
- Structural Changes During Oxygen Binding- When oxygen binds to one heme group, a small change takes place in the arrangement of the protein subunits. These structural changes increase the oxygen-binding affinity of the remaining sites. This property is referred to as “cooperative binding”.
Types of Human Hemoglobin
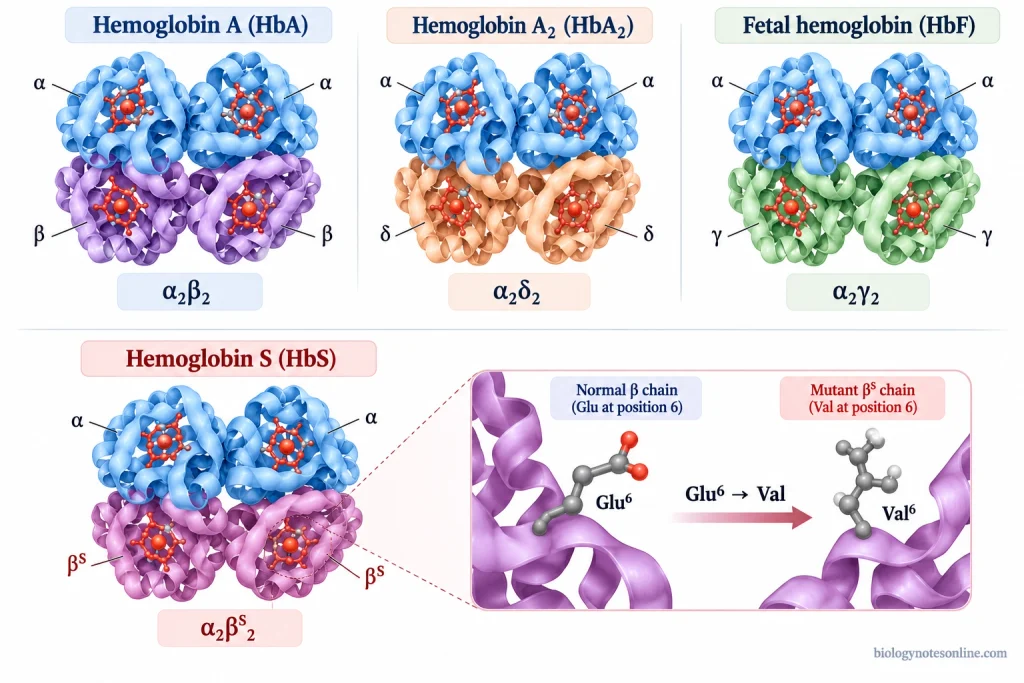
Different types of human hemoglobin (Hb) are formed depending on the combination of globin chains present in the molecule. The three major physiological types are HbA, HbA2 and HbF.
1. Hemoglobin A (HbA)
HbA is the predominant type of Hb found in normal adult blood. It is made up of two alpha (α) and two beta (β) globin chains (α₂β₂). About 95-98% of the total Hb in healthy adults consists of this type, which carries most of the oxygen in adult blood.
2. Hemoglobin A2 (HbA2)
A small fraction of adult Hb is made up of HbA2. Unlike HbA, it contains two alpha (α) and two delta (δ) globin chains (α₂δ₂).
It is the minor adult form, normally accounting for about 2-3% of the total Hb.
3. Fetal Hemoglobin (HbF)
HbF is the major type of Hb present during fetal development. Its structure consists of two alpha (α) and two gamma (γ) globin chains (α₂γ₂). It has a higher affinity for oxygen compared to HbA, which allows the fetus to take up oxygen from the maternal blood through the placenta.
After birth, the production of gamma chains gradually decreases, while beta-chain production increases. During this period, HbF is replaced by HbA. Only a small amount of HbF is normally present in adult blood.
4. Abnormal Hemoglobin Variants
Certain inherited mutations in the globin genes result in the formation of structurally different Hb molecules. These are referred to as “hemoglobin variants”. Some variants have little or no clinical effect, whereas others may affect the normal functioning of Hb.
One of the clinically important examples is hemoglobin S (HbS). In this variant, the amino acid glutamic acid is replaced by valine at the sixth position of the beta-globin chain. Under low-oxygen conditions, HbS can form aggregates that alter the normal shape of red blood cells.
The presence of an abnormal Hb variant is different from an abnormal Hb concentration. A structural variant involves changes in the protein itself, whereas Hb concentration refers to the amount of Hb present in a given volume of blood.
Hemoglobin Production
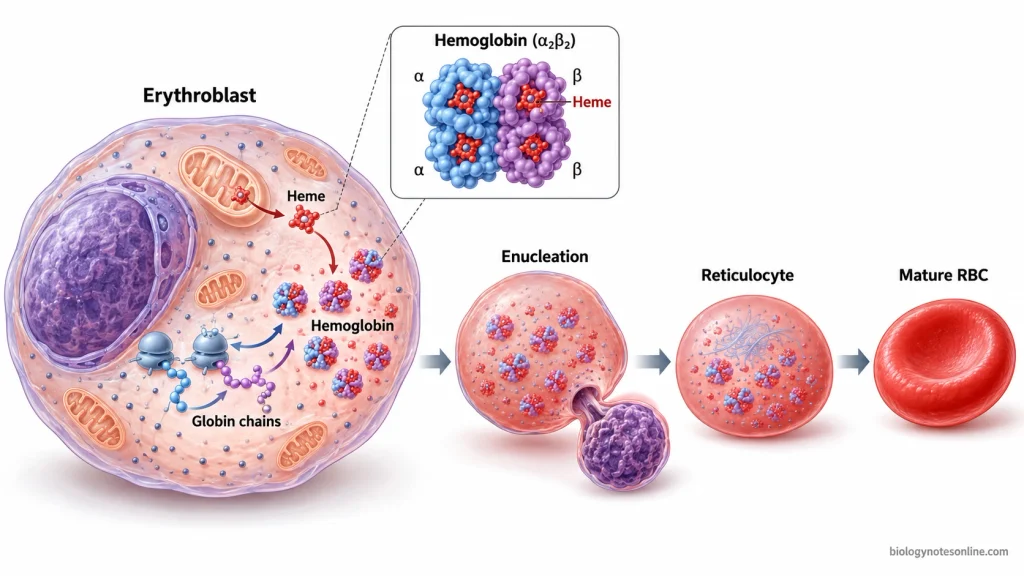
Hemoglobin (Hb) is produced during the development of red blood cells (RBCs) in the bone marrow. The process involves the synthesis of two components, heme and globin chains, which are produced simultaneously in developing erythroblasts. Heme is synthesised in the mitochondria and cytoplasm, whereas globin chains are formed by the ribosomes.
The major steps involved in Hb production are as follows-
1. Formation and Development of Erythroblasts
The process begins with the development of erythroid progenitor cells into erythroblasts in the bone marrow. Their survival and maturation are stimulated by the hormone erythropoietin (EPO), which is mainly produced by the kidneys. During erythroblast development, the cells gradually increase Hb production.
2. Uptake of Iron
Developing erythroblasts take up iron from the blood, where it is transported by a protein called transferrin. Iron enters the cells through transferrin receptor 1 (TfR1). It is then transported into the mitochondria for heme synthesis.
3. Initiation of Heme Synthesis
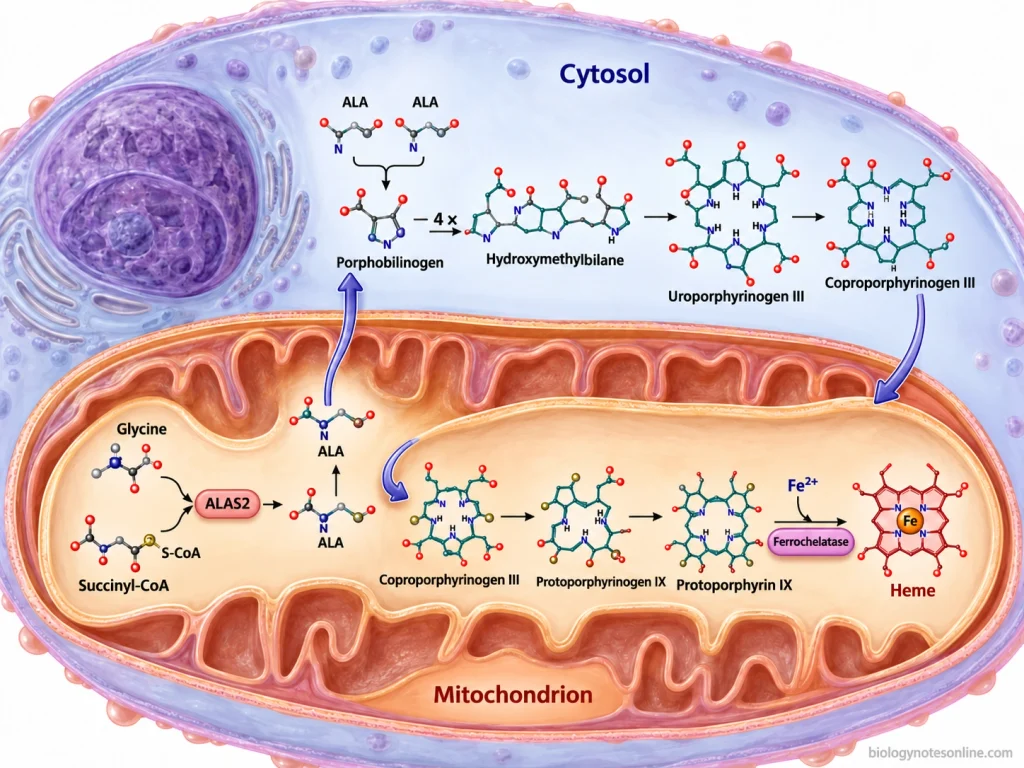
The first reaction of heme synthesis takes place in the mitochondrial matrix. Here, glycine combines with succinyl-coenzyme A (succinyl-CoA) to form 5-aminolevulinic acid (ALA).
This reaction is catalysed by the enzyme erythroid 5-aminolevulinate synthase (ALAS2). It is the initial rate-limiting step of heme synthesis.
4. Formation of Porphyrin Intermediates
The ALA formed in the mitochondria is transported into the cytoplasm, where further enzymatic reactions take place.
Two molecules of ALA combine to form one molecule of porphobilinogen (PBG) by the action of the enzyme ALA dehydratase. Four molecules of PBG are then combined to form hydroxymethylbilane. This is converted into uroporphyrinogen III and subsequently into coproporphyrinogen III.
5. Completion of Heme Synthesis
Coproporphyrinogen III is transported back into the mitochondria for further reactions. It is first converted into protoporphyrinogen IX, which is then oxidised to form protoporphyrin IX.
In the final step, ferrous iron (Fe²⁺) is incorporated into protoporphyrin IX by the enzyme ferrochelatase (FECH). The product formed is heme.
6. Synthesis of Globin Chains
Along with heme synthesis, globin chains are produced by the ribosomes present in the cytoplasm of developing erythroblasts.
The alpha (α) and beta (β) globin chains are synthesised from amino acids according to the genetic instructions. Their production is regulated along with heme synthesis. Heme also controls the translation of globin chains, preventing excessive production when sufficient heme is not available.
7. Formation of Hemoglobin
The newly synthesised globin chains fold into their specific structures and associate with heme groups. Each globin chain contains one heme group.
In adult Hb, two α and two β globin chains are assembled into a tetrameric structure. The four globin chains together contain four heme groups.
8. Hemoglobin Accumulation and RBC Maturation
During further erythroblast development, Hb gradually accumulates in the cytoplasm. The nucleus is expelled as the erythroblast develops into an immature RBC called a “reticulocyte”.
Reticulocytes still contain ribosomes and continue the synthesis of Hb. During maturation, they lose the remaining ribosomes and other cellular organelles. Mature RBCs lack the machinery required for further Hb synthesis.
Normal Hemoglobin Levels
The normal hemoglobin (Hb) level varies depending on age, sex and certain physiological conditions. It is measured in grams per deciliter (g/dL) of whole blood. The reference ranges may also differ between laboratories, depending on the testing method and the reference population.
Normal Hemoglobin Levels in Adults
The Hb concentration is generally higher in adult males compared to adult females. Different reference ranges are used for both groups.
The following are the adult reference ranges according to the University of Iowa laboratory handbook.
| Adult Population | Normal Hb Level (g/dL) |
|---|---|
| Adult males (18 years and above) | 13.2–17.7 |
| Adult females (18 years and above) | 11.9–15.5 |
Some factors affecting the adult Hb concentration are-
- Sex- Adult males generally have a higher Hb concentration than females. The laboratory reference intervals are also different for both groups.
- Pregnancy- During pregnancy, the plasma volume increases more than the red blood cell mass, which causes a decrease in Hb concentration. The normal reference values for non-pregnant adults are not directly applicable during pregnancy.
- Laboratory Variation- Different laboratories may have slightly different normal ranges. For example, Oregon Health & Science University uses 13.5–17.5 g/dL for adult males and 12.0–16.0 g/dL for adult females.
Hemoglobin Levels by Age
The Hb concentration changes considerably during the early stages of life. These variations are observed in the following age groups-
- Newborns- Newborn babies have a relatively high Hb concentration at birth. The level gradually decreases during the first few months of life.
- Infants- During infancy, Hb levels are lower compared to those of newborns. The reference range changes rapidly in the first six months.
- Children- The Hb concentration gradually increases with age. Different ranges are used for young children and adolescents, with separate male and female reference values during adolescence.
The following are the age-specific reference ranges provided by the University of Iowa laboratory handbook.
| Age Group | Male (g/dL) | Female (g/dL) |
|---|---|---|
| 0–30 days | 13.4–19.9 | 13.4–19.9 |
| 31 days to less than 2 months | 10.7–17.1 | 10.7–17.1 |
| 2 to less than 3 months | 9.0–14.1 | 9.0–14.1 |
| 3 to less than 6 months | 9.5–14.1 | 9.5–14.1 |
| 6 months to less than 1 year | 11.3–14.1 | 11.3–14.1 |
| 1 to less than 5 years | 10.9–15.0 | 10.9–15.0 |
| 5 to less than 11 years | 11.9–15.0 | 11.9–15.0 |
| 11 to less than 18 years | 12.7–17.0 | 11.9–15.0 |
The reference values given for infants below six months apply to full-term infants. Premature infants may require different reference ranges. The Hb result is interpreted according to the reference interval provided by the testing laboratory and the clinical condition of the individual.
Factors Affecting Hemoglobin Levels
The concentration of hemoglobin (Hb) in blood is influenced by various physiological, nutritional and environmental factors. Some of the important factors affecting Hb levels are as follows-
- Age- The Hb concentration varies at different stages of life. Newborn babies have relatively high Hb levels, which gradually decrease during the first few months after birth. This is referred to as “physiological anemia of infancy”. The concentration then increases during childhood and reaches adult levels with growth.
- Sex- Adult males generally have higher Hb concentrations compared to adult females. This difference is partly associated with the hormone testosterone, which stimulates the production of red blood cells (RBCs).
- Pregnancy- During pregnancy, the plasma volume increases more than the RBC mass. This causes dilution of the blood, resulting in a decrease in the measured Hb concentration. The process is known as “hemodilution”.
- Nutritional Factors- Iron is an essential component required for the synthesis of Hb. Its deficiency affects normal Hb production and may lead to iron deficiency anemia. Other nutrients, particularly vitamin B12 and folate, are required for the normal formation and maturation of RBCs. Deficiency of these vitamins can also result in decreased Hb concentration.
- High Altitude- People living at high altitudes generally have higher Hb levels compared to those living at sea level. At higher altitudes, the reduced availability of oxygen stimulates the release of erythropoietin (EPO), which increases RBC production in the bone marrow. The Hb concentration gradually increases during prolonged exposure to these conditions.
- Smoking- Cigarette smoking may increase the Hb concentration. Carbon monoxide present in cigarette smoke binds to Hb and reduces its oxygen-carrying capacity. In response to the reduced oxygen availability, the body may increase the production of RBCs.
- Hydration- The amount of water present in the blood also affects the measured Hb concentration. During dehydration, plasma volume decreases, which may produce an apparently high Hb level without an increase in the total amount of Hb. An increase in plasma volume, on the other hand, can lower its measured concentration.
- Kidney Function– The kidneys produce EPO, a hormone responsible for stimulating RBC production in the bone marrow. In chronic kidney disease, the production of this hormone may decrease. It results in reduced RBC formation and may lower the Hb concentration.
- Chronic Diseases and Inflammation- Certain chronic diseases, infections and inflammatory conditions may affect the normal production of Hb. During inflammation, iron availability for RBC production is reduced, even when sufficient iron is stored in the body. Inflammatory substances can also suppress RBC formation and reduce their survival.
- Blood Loss and RBC Destruction- Excessive blood loss during injuries, heavy menstruation or internal bleeding can decrease the Hb concentration. In certain disorders, RBCs are destroyed faster than they are produced. This condition is referred to as “hemolysis” and may also result in a reduction of Hb levels.
Causes of Low Hemoglobin
Hemoglobin (Hb) is the iron containing pigment of the red blood cells (RBCs) that transports oxygen to the tissues. A low level of Hb in blood is termed as anemia. It can develop when the RBCs are produced in less amount, destroyed faster, or lost from the circulation. The following are some of the important causes of low hemoglobin:
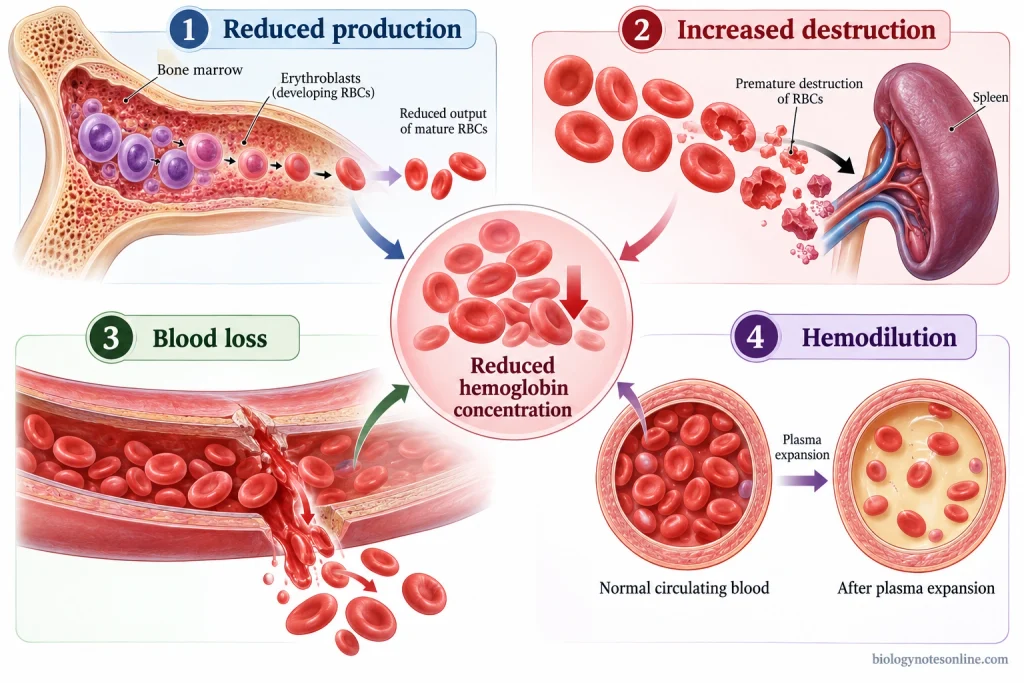
1. Decreased production of RBCs
- Iron deficiency is the most common cause of low hemoglobin in the world. Iron is required for the heme portion of the Hb molecule, its deficiency is mostly seen with a poor diet, malabsorption and chronic blood loss.
- Deficiency of vitamin B12 (cyanocobalamin) or folic acid causes megaloblastic anemia. In this condition the DNA synthesis of developing RBCs gets affected, and large immature cells are released into the blood.
- Chronic kidney disease also lowers the Hb level. Erythropoietin (EPO) is secreted mainly by the kidneys, so a damaged kidney produces less EPO and the RBC formation is slowed down.
- Bone marrow disorders like aplastic anemia, leukemia and myelodysplastic syndrome, in which the marrow fails to generate enough RBCs.
- Anemia of chronic disease – develops in long standing conditions like tuberculosis, rheumatoid arthritis and cancers. The iron stores remain adequate here, but its utilization by the marrow is impaired.
- Hypothyroidism. The thyroid hormones stimulate erythropoiesis, their deficiency therefore reduces the RBC output.
- Lead poisoning, lead inhibits the enzymes of heme synthesis and Hb formation is disturbed.
2. Increased destruction of RBCs (hemolysis)
- Hereditary disorders like thalassemia, sickle cell anemia, hereditary spherocytosis and glucose-6-phosphate dehydrogenase (G6PD) deficiency.
- Autoimmune hemolytic anemia, where the RBC’s membrane gets coated by antibodies and the cells are destroyed mostly in the spleen.
- Infections like malaria, in which Plasmodium multiplies inside the RBCs and ruptures them. Certain drugs and snake venom can also produce hemolysis etc.
3. Blood loss
- Heavy menstrual bleeding (menorrhagia) is a very common cause in females.
- Gastrointestinal (GI) bleeding from peptic ulcers, hemorrhoids or hookworm infestation (Ancylostoma duodenale, Necator americanus).
- Trauma, surgery or any injury associated with massive hemorrhage.
4. Pregnancy
- During pregnancy the plasma volume is expanded, the Hb gets diluted because of that. This is a physiological cause and it is not a true reduction in the red cell mass.
Symptoms of Low Hemoglobin
The symptoms of low hemoglobin (Hb) vary with the severity and how rapidly its concentration decreases. Mild cases may have no noticeable symptoms. Some symptoms are observed only during physical activities, whereas in severe anemia, they may occur even at rest.
The common symptoms of low Hb are as follows-
- Fatigue and Weakness- A person may feel tired and weak even after performing normal daily activities. The capacity to perform physical work may also decrease.
- Shortness of Breath- During physical activities, more oxygen is required by the body. When the oxygen-carrying capacity of blood is reduced, a person may experience difficulty in breathing. It is referred to as “dyspnea”. In severe anemia, breathlessness may occur even at rest.
- Pale Skin- The skin, nail beds and inner surface of the eyelids (conjunctiva) may appear pale. This clinical sign is called “pallor”. It is more noticeable in severe cases.
- Increased Heart Rate- In low Hb, the heart may beat faster to maintain the oxygen supply to different tissues of the body. Some individuals also experience a rapid or pounding heartbeat, which is referred to as “palpitations”.
- Dizziness and Headache- Headaches are also reported in individuals having low Hb. Dizziness or lightheadedness may occur, particularly during physical activities or while standing up.
- Cold Hands and Feet- In some individuals, the hands and feet may feel unusually cold.
- Difficulty in Concentration- Reduced mental alertness and difficulty in concentration may be observed in individuals with low Hb. These problems are also found in certain types of anemia, particularly those associated with iron deficiency.
- Chest Pain and Fainting- In severe anemia, the reduced oxygen supply may cause chest pain, especially in individuals having an underlying heart disease. Fainting (syncope) may also occur. These symptoms require urgent medical attention.
Functions of Hemoglobin
The major functions of hemoglobin (Hb) are as follows-
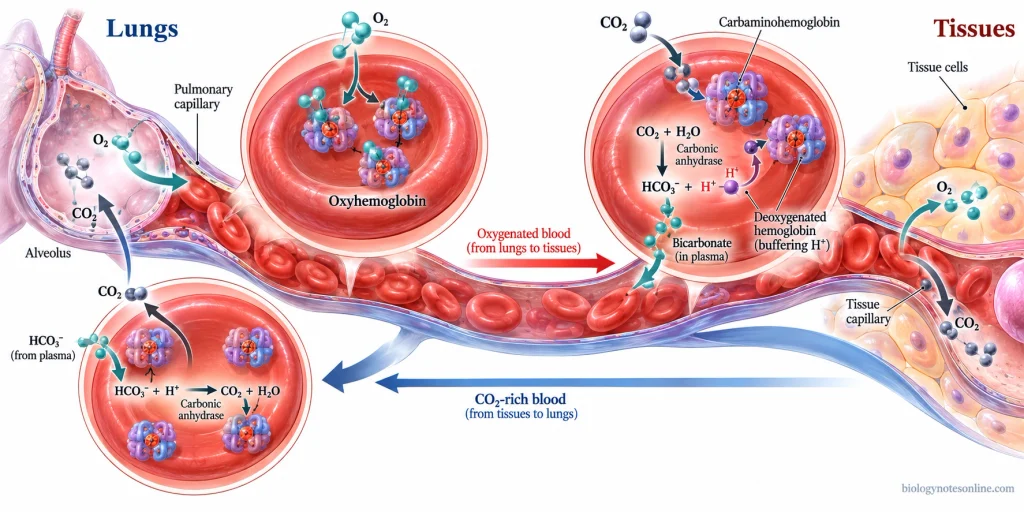
- Transport of Oxygen- The primary function of Hb is to carry oxygen from the lungs to different tissues of the body. In the lungs, oxygen binds to Hb, forming “oxyhemoglobin”. The oxygen is then released in the body tissues, where it is utilised by the cells for cellular respiration.
- Transport of Carbon Dioxide- A portion of carbon dioxide (CO₂) produced during cellular metabolism is carried by Hb from the body tissues to the lungs. It binds to the globin portion of Hb, forming a compound called “carbaminohemoglobin”. In the lungs, CO₂ is released and removed from the body during exhalation. However, most of the CO₂ is transported in the blood in the form of bicarbonate.
- Maintenance of Blood pH- Hb also acts as a buffer and plays an important role in maintaining the acid-base balance of blood. During CO₂ transport, hydrogen ions (H⁺) are formed, which are taken up by Hb to prevent excessive changes in blood pH. When oxygen binds to Hb in the lungs, these ions are released and combine with bicarbonate to form CO₂, which is then exhaled.
References
- Ahmed, M. H., Ghatge, M. S., & Safo, M. K. (2020). Hemoglobin: Structure, function and allostery. In U. Hoeger & J. R. Harris (Eds.), Vertebrate and invertebrate respiratory proteins, lipoproteins and other body fluid proteins (Subcellular Biochemistry, Vol. 94, pp. 345–382). Springer. https://doi.org/10.1007/978-3-030-41769-7_14
- Ahmed, S. G., & Ibrahim, U. A. (2021). Non-S sickling hemoglobin variants: Historical, genetic, diagnostic, and clinical perspectives. Oman Medical Journal, 36(3), e261. https://doi.org/10.5001/omj.2021.102
- Allen, L. H., Miller, J. W., de Groot, L., Rosenberg, I. H., Smith, A. D., Refsum, H., & Raiten, D. J. (2018). Biomarkers of Nutrition for Development (BOND): Vitamin B-12 review. The Journal of Nutrition, 148(Suppl. 4), 1995S–2027S. https://doi.org/10.1093/jn/nxy201
- Barbarani, G., Labedz, A., Stucchi, S., Abbiati, A., & Ronchi, A. E. (2021). Physiological and aberrant γ-globin transcription during development. Frontiers in Cell and Developmental Biology, 9, 640060. https://doi.org/10.3389/fcell.2021.640060
- Batchelor, E. K., Kapitsinou, P., Pergola, P. E., Kovesdy, C. P., & Jalal, D. I. (2020). Iron deficiency in chronic kidney disease: Updates on pathophysiology, diagnosis, and treatment. Journal of the American Society of Nephrology, 31(3), 456–468. https://doi.org/10.1681/ASN.2019020213
- Begum, S., & Latunde-Dada, G. O. (2019). Anemia of inflammation with an emphasis on chronic kidney disease. Nutrients, 11(10), 2424. https://doi.org/10.3390/nu11102424
- Betts, J. G., Young, K. A., Wise, J. A., Johnson, E., Poe, B., Kruse, D. H., Korol, O., Johnson, J. E., Womble, M., & DeSaix, P. (2013). Anatomy and physiology. OpenStax. https://openstax.org/books/anatomy-and-physiology/pages/1-introduction
- Betts, J. G., Young, K. A., Wise, J. A., Johnson, E., Poe, B., Kruse, D. H., Korol, O., Johnson, J. E., Womble, M., & DeSaix, P. (2022). Anatomy and physiology 2e. OpenStax. https://openstax.org/books/anatomy-and-physiology-2e/pages/1-introduction
- Bhoopalan, S. V., Huang, L. J.-S., & Weiss, M. J. (2020). Erythropoietin regulation of red blood cell production: From bench to bedside and back. F1000Research, 9, 1153. https://doi.org/10.12688/f1000research.26648.1
- Billett, H. H. (1990). Hemoglobin and hematocrit. In H. K. Walker, W. D. Hall, & J. W. Hurst (Eds.), Clinical methods: The history, physical, and laboratory examinations (3rd ed., Chapter 151). Butterworths. https://www.ncbi.nlm.nih.gov/books/NBK259/
- Brittenham, G. M., Moir-Meyer, G., Abuga, K. M., Datta-Mitra, A., Cerami, C., Green, R., Pasricha, S.-R., & Atkinson, S. H. (2023). Biology of anemia: A public health perspective. The Journal of Nutrition, 153(Suppl. 1), S7–S28. https://doi.org/10.1016/j.tjnut.2023.07.018
- Chandra, S., Tripathi, A. K., Mishra, S., Amzarul, M., & Vaish, A. K. (2012). Physiological changes in hematological parameters during pregnancy. Indian Journal of Hematology and Blood Transfusion, 28(3), 144–146. https://doi.org/10.1007/s12288-012-0175-6
- Chaparro, C. M., & Suchdev, P. S. (2019). Anemia epidemiology, pathophysiology, and etiology in low- and middle-income countries. Annals of the New York Academy of Sciences, 1450(1), 15–31. https://doi.org/10.1111/nyas.14092
- Chiabrando, D., Mercurio, S., & Tolosano, E. (2014). Heme and erythropoieis: More than a structural role. Haematologica, 99(6), 973–983. https://doi.org/10.3324/haematol.2013.091991
- Chung, J., Chen, C., & Paw, B. H. (2012). Heme metabolism and erythropoiesis. Current Opinion in Hematology, 19(3), 156–162. https://doi.org/10.1097/MOH.0b013e328351c48b
- Dailey, H. A., & Meissner, P. N. (2013). Erythroid heme biosynthesis and its disorders. Cold Spring Harbor Perspectives in Medicine, 3(4), a011676. https://doi.org/10.1101/cshperspect.a011676
- Foord, E., Sairafi, D., Berg, M., Westerling, S., Adigun, T., Uzunel, M., Papasavva, T., & Uhlin, M. (2026). Decoding thalassemia and sickle cell disease: Advances in molecular technologies for comprehensive variant detection. Frontiers in Genetics, 17, 1810737. https://doi.org/10.3389/fgene.2026.1810737
- Gangakhedkar, G. R., & Kulkarni, A. P. (2021). Physiological changes in pregnancy. Indian Journal of Critical Care Medicine, 25(Suppl. 3), S189–S192. https://doi.org/10.5005/jp-journals-10071-24039
- Handelsman, D. J., Hirschberg, A. L., & Bermon, S. (2018). Circulating testosterone as the hormonal basis of sex differences in athletic performance. Endocrine Reviews, 39(5), 803–829. https://doi.org/10.1210/er.2018-00020
- Hanna, R. M., Streja, E., & Kalantar-Zadeh, K. (2021). Burden of anemia in chronic kidney disease: Beyond erythropoietin. Advances in Therapy, 38(1), 52–75. https://doi.org/10.1007/s12325-020-01524-6
- Karakochuk, C. D., Hess, S. Y., Moorthy, D., Namaste, S., Parker, M. E., Rappaport, A. I., Wegmüller, R., Dary, O., & HEmoglobin MEasurement (HEME) Working Group. (2019). Measurement and interpretation of hemoglobin concentration in clinical and field settings: A narrative review. Annals of the New York Academy of Sciences, 1450(1), 126–146. https://doi.org/10.1111/nyas.14003
- Kim, Y., Park, J., & Kim, M. (2017). Diagnostic approaches for inherited hemolytic anemia in the genetic era. Blood Research, 52(2), 84–94. https://doi.org/10.5045/br.2017.52.2.84
- Koury, M. J., & Haase, V. H. (2015). Anaemia in kidney disease: Harnessing hypoxia responses for therapy. Nature Reviews Nephrology, 11(7), 394–410. https://doi.org/10.1038/nrneph.2015.82
- Kuhn, V., Diederich, L., Keller, T. C. S., IV, Kramer, C. M., Lückstädt, W., Panknin, C., Suvorava, T., Isakson, B. E., Kelm, M., & Cortese-Krott, M. M. (2017). Red blood cell function and dysfunction: Redox regulation, nitric oxide metabolism, anemia. Antioxidants & Redox Signaling, 26(13), 718–742. https://doi.org/10.1089/ars.2016.6954
- Kumar, A., Sharma, E., Marley, A., Samaan, M. A., & Brookes, M. J. (2022). Iron deficiency anaemia: Pathophysiology, assessment, practical management. BMJ Open Gastroenterology, 9(1), e000759. https://doi.org/10.1136/bmjgast-2021-000759
- Long, B., & Koyfman, A. (2018). Emergency medicine evaluation and management of anemia. Emergency Medicine Clinics of North America, 36(3), 609–630. https://doi.org/10.1016/j.emc.2018.04.009
- McPhedran, P., & Hall, R. B. (2005). Evaluation of anemia in adults: Going after the common causes [Conference abstract]. Blood, 106(11), 3769. https://doi.org/10.1182/blood.V106.11.3769.3769
- Nagatomo, S., Nagai, M., & Kitagawa, T. (2022). Structural origin of cooperativity in human hemoglobin: A view from different roles of α and β subunits in the α₂β₂ tetramer. Biophysical Reviews, 14(2), 483–498. https://doi.org/10.1007/s12551-022-00945-7
- Nairz, M., Theurl, I., Wolf, D., & Weiss, G. (2016). Iron deficiency or anemia of inflammation? Differential diagnosis and mechanisms of anemia of inflammation. Wiener Medizinische Wochenschrift, 166(13–14), 411–423. https://doi.org/10.1007/s10354-016-0505-7
- Ng, I. K. S., Choong, C., Lim, S. L., & See, K. C. (2025). Management of anaemia in critically ill adults. Singapore Medical Journal, 66(5), 283–290. https://doi.org/10.4103/singaporemedj.SMJ-2024-005
- Otto, J. M., Montgomery, H. E., & Richards, T. (2013). Haemoglobin concentration and mass as determinants of exercise performance and of surgical outcome. Extreme Physiology & Medicine, 2, Article 33. https://doi.org/10.1186/2046-7648-2-33
- Sankaran, V. G., & Weiss, M. J. (2015). Anemia: Progress in molecular mechanisms and therapy. Nature Medicine, 21(3), 221–230. https://doi.org/10.1038/nm.3814
- Sharma, A. J., Addo, O. Y., Mei, Z., & Suchdev, P. S. (2019). Reexamination of hemoglobin adjustments to define anemia: Altitude and smoking. Annals of the New York Academy of Sciences, 1450(1), 190–203. https://doi.org/10.1111/nyas.14167
- Siebenmann, C., Roche, J., Schlittler, M., Simpson, L. L., & Stembridge, M. (2024). Regulation of haemoglobin concentration at high altitude. The Journal of Physiology, 602(21), 5587–5600. https://doi.org/10.1113/JP284578
- Thom, C. S., Dickson, C. F., Gell, D. A., & Weiss, M. J. (2013). Hemoglobin variants: Biochemical properties and clinical correlates. Cold Spring Harbor Perspectives in Medicine, 3(3), a011858. https://doi.org/10.1101/cshperspect.a011858
- Wajcman, H., & Moradkhani, K. (2011). Abnormal haemoglobins: Detection & characterization. The Indian Journal of Medical Research, 134(4), 538–546. https://pmc.ncbi.nlm.nih.gov/articles/PMC3237254/
- Weiss, G., Ganz, T., & Goodnough, L. T. (2019). Anemia of inflammation. Blood, 133(1), 40–50. https://doi.org/10.1182/blood-2018-06-856500
- Widness, J. A. (2008). Pathophysiology of anemia during the neonatal period, including anemia of prematurity. NeoReviews, 9(11), e520. https://doi.org/10.1542/neo.9-11-e520